In April 2026, Anaor Saawuan laid her eight-month-old granddaughter on a thin mattress inside their makeshift shelter at the Anyiin Internally Displaced Persons (IDP) camp in Logo Local Government Area of Benue State, Central Nigeria.
The infant had been vomiting and stooling for two days. She also had a fever. Grandma thought it was a teething problem, so she gave her a cough syrup and tablets she bought at a patent medicine shop across the road.
But when the vomiting and diarrhoea returned, she took the child to a hospital outside the camp, where health workers said she needed a blood transfusion.
“I had no money,” she said. “And there was nobody to help me.”
She resorted to a traditional remedy. However, at about 9 p.m. on 2 May, the child died. She believes the child might have survived if the nearby clinic within the camp had still been operational.
“There used to be a clinic here,” Mrs Saawuan said, pointing towards a building inside the camp. “Medicines were available, and treatment was free, until everything stopped.”


Her case illustrates the healthcare crisis at settlements for people displaced by conflicts in Benue State, where clinics are closed or poorly equipped, medicines are in short supply, referral systems are weak, and many families cannot afford healthcare costs.
Another health burden
Mrs Saawuan also has a young grandson, who was diagnosed with an inguinal hernia and referred for surgery at a general hospital. “We barely feed,” she said. “How can I pay for an operation?”
Mrs Saawuan has again resorted to herbs to manage his condition.


A risky pregnancy
A few shelters away in the same camp lives a pregnant 32-year-old woman, Naomi Teryen.


Her previous pregnancies were difficult, she said, involving prolonged labour and Caesarean sections.
But five months into her current pregnancy, she has little money for regular antenatal care at a health centre outside the camp and has not had an ultrasound scan.
“I don’t have a job, and there is no proper healthcare service in this camp,” she told PREMIUM TIMES.
Mrs Teryen said she previously relied on the health facility in the camp.
“When the hospital was available, we used to get medicine free of charge there,” she said. “But now that the hospital has been closed, when we go to the health centre, we pay for medicine.”
Cost of a closed clinic
Mrs Teryen showed PREMIUM TIMES the medicines she received during an antenatal visit. They consisted of paracetamol and Multiple Micronutrient Supplements (MMS), which contain vitamins and minerals intended to prevent micronutrient deficiencies and improve maternal and birth outcomes.
The MMS supplements are distributed through Nigeria’s public health system with support from the government and development partners, including UNICEF.
They are intended to be dispensed free of charge. But Mrs Teryen alleged pregnant women from the camp are charged for medicines, including MMS, during antenatal visits to the health centre outside the camp.
She said that an antenatal visit to the European Economic Community Health Clinic (CHC) in Anyiin, a government-owned primary healthcare facility in the community, typically costs her about ₦3,000. She recalled an occasion when she arrived at the centre with only ₦1,000. “They told me to go back,” she said.


Mrs Teryen’s husband makes wooden crafts inside the camp. But he often sells nothing.
“Every time she gives birth, it is difficult. Sometimes we spend more than a week in the hospital,” he said.
Terrence Akighir, a medical doctor and UNICEF consultant, told PREMIUM TIMES the supplements should not be sold to patients.
“MMS is supposed to be free,” he said. “If somebody is taking advantage of that to sell the medicine, it should be looked into and stopped. These women do not have money. If they are paying for medicines that should be free, how will they meet their other healthcare needs?”
A UNICEF humanitarian report corroborates Mr Akighir’s claims amid the humanitarian crisis.
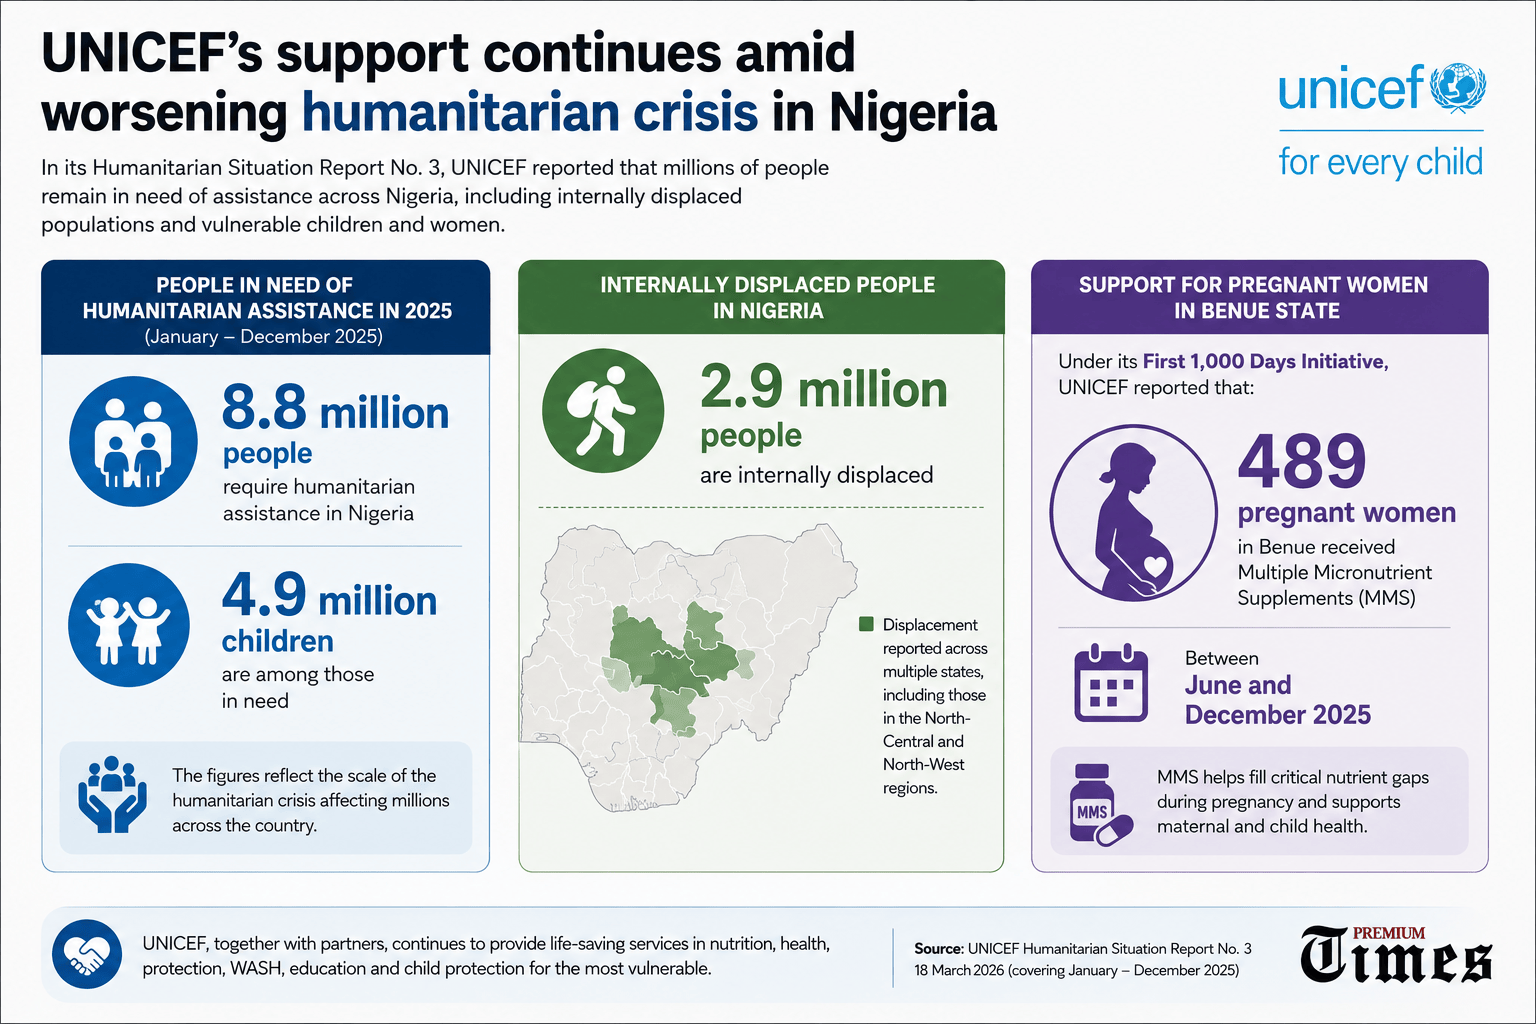
In its Humanitarian Situation Report No. 3, published on 18 March 2026 and covering January to December 2025, the agency said that 8.8 million people, including 4.9 million children, required humanitarian assistance, while 2.9 million people were internally displaced.
UNICEF reported that, under its First 1,000 Days Initiative, 489 pregnant women in Benue IDPs received free MMS between June and December 2025.
Clinic declines comment
PREMIUM TIMES contacted the European Economic Community Health Clinic in Anyiin for a response to the allegation. An official on duty said she was not authorised to comment on whether MMS were being sold to patients and declined to provide further information before walking away.

When the clinic closed
The healthcare crisis at the Anyiin IDP camp did not begin this year. It followed the closure of a health facility inside the camp that had once provided basic medical care to displaced residents.
Helen Tsavwua, a former worker at the facility, said the clinic was established by Médecins Sans Frontières (MSF), which provided medical services to displaced communities in Anyiin IDP at the height of the displacement crisis in 2018.
“When MSF was leaving, Victim Support Fund (VSF) took over until January 2021,” she said. “When they left, the hospital was closed down.”
According to Ms Tsavwua, VSF continued to provide some medicines to support patients, but the absence of medical personnel meant that residents could not reliably access treatment.
“They were giving medicines, but there was no doctor to attend to patients,” she said. “When children or women were sick, they would go there, but there was nobody to give them medicine.”
She said the limited treatment available at the time was also inadequate for some patients.
“Sometimes only malaria medicine or paracetamol would be given without even testing,” she said.
A community health worker at the Community Health Clinic, Anyiin, who previously worked at the camp facility, also attributed its closure to a lack of funding. The worker asked not to be named because of concerns about possible victimisation.
According to the health worker, MSF had provided substantial support to the facility, including medical personnel. Some of the doctors and other health workers who had worked under the organisation were retained when its support ended, but sustaining the facility became increasingly difficult.
“When MSF left, it became difficult to sustain the hospital,” the worker said. “Medicine stopped coming in, and we were asked to return to our former posts.”
The worker said the camp’s health services had depended heavily on support from humanitarian organisations and other non-governmental groups.
“Most of the activities in the camp, especially health and food, were supported by NGOs,” the worker said, adding that the government’s role through the Benue State Emergency Management Agency (SEMA) was largely supervisory.
An abandoned clinic
PREMIUM TIMES visited the former clinic located within the NKST Primary School, Anyiin, where internally displaced people still live. The facility appeared deserted, with its rooms locked and no health workers or patients present. Its beige-and-black walls were chipped and peeling, while faded chalk inscriptions remained on the dark metal doors. The concrete walkway was cracked and stained, bordered by bare reddish soil, while children moved through the surrounding school grounds.


Camp residents said medicines supplied by non-profit organisations were still kept inside the locked facility. They said the drugs remained inaccessible because the building was closed and no health workers were available to attend to patients.
MSF exits Benue
PREMIUM TIMES contacted Abdulkareem Yakubu, field communication officer and spokesperson for MSF in Nigeria, for clarification on the organisation’s withdrawal and its implications for communities previously served by its teams.
Mr Yakubu said he could not comment on the current situation in communities where MSF had ended its activities because the organisation had closed its project in Benue. He referred PREMIUM TIMES to MSF’s formal statement on the closure, which he shared with the newspaper, saying the statement contained the organisation’s position on its decision to leave the state.
In the statement, MSF said it had decided to phase out its medical humanitarian activities in Benue after six years of providing healthcare to internally displaced people and host communities. The organisation said basic healthcare and decentralised activities would conclude by the end of June 2024, while family planning and sexual and reproductive healthcare activities would cease by the end of Jul,y and comprehensive sexual and gender-based violence care would end in August the same year.
“MSF operations’ core mission is to provide urgent medical humanitarian assistance in emergency contexts, and we have a responsibility to ensure this capacity to provide assistance at a moment’s notice is maintained,” the statement said.
The organisation said the decision was made after considering medical needs across Nigeria and the need to reinforce MSF’s response in other parts of the country.
“We remain concerned for the safety of women and girls in Benue,” the statement read. “We will continue to advocate for more action by the Nigerian government and the newly arrived international organisations present in the area, to recognise the threat that SGBV poses to displaced people and to provide survivors with the necessary care.”
MSF said that between May 2018 and March 2024, its medical teams conducted 412,832 consultations and treated 223,871 patients in Mbawa, Ortese, Naka and Agagbe camps and host communities. The organisation also said it admitted 1,731 people following instances of sexual and gender-based violence in 2023.
“The arrival of international organisations is a hopeful signal that MSF’s drive to recognise the plight of displaced people in Benue state is being heard,” the statement added.
According to MSF, a new clinic supported by UNICEF and WHO began operating in three camps in late 2023. The organisation said the development offered some prospect of continued healthcare support for displaced communities after its withdrawal.
After MSF’s exit
At the Anyiin IDP camp, the effects of MSF’s departure have continued to be felt by displaced residents. Julius Tema, chairman of the Anyiin IDP camp, said the withdrawal of the organisation and the subsequent closure of the camp’s health facility had left residents struggling to access basic healthcare.
“Our biggest challenges now are food and health,” he said. “There are many sick people in this camp.”
He said malaria remained widespread, alongside cases of hepatitis and other illnesses.
“There was a hospital here before,” Mr Tema said. “Today, that hospital is no longer functioning. We don’t have medicines anymore.”
With no functioning clinic, residents must seek treatment outside the camp, a burden many cannot afford.
“When there is no medicine and no hospital inside the camp, people suffer,” he said. “Some simply resort to herbs because they don’t have money to seek treatment elsewhere.”
Mr Tema said pregnant women, children and older residents were particularly affected and appealed to the government and humanitarian organisations to restore healthcare services.
“We need medicines. We need medical personnel. We need intervention before more lives are lost,” he said.
Officials stay silent
The agencies responsible for managing the IDP camps and providing healthcare to Benue residents did not respond to PREMIUM TIMES’ requests for comments on the findings of this investigation.
During a telephone conversation on 7 July, James Iorpuu, executive secretary of the Benue State Emergency Management Agency (SEMA), which oversees IDP camps, scheduled a meeting at the agency’s headquarters in Makurdi for 9 a.m. the following day.
The reporter arrived before the scheduled time and waited for more than three hours. But when, at about noon, Mr Iorpuu emerged from his office, he ignored the reporter’s presence, entered his vehicle, and drove away without granting the interview or proposing another time.
PREMIUM TIMES subsequently sent questions to SEMA about the closure of the health facility within the IDP camp, the shortage of medicines and medical supplies, healthcare costs borne by displaced residents, emergency referral arrangements, and support for health workers serving the camps.
As of the time of this publication, the agency has not responded.


The Benue State Commissioner for Health, Paul Ogwuche, also did not respond to repeated requests for comment. During a visit to the ministry at the Benue State Secretariat, Mr Ogwuche’s secretary requested a formal written interview request, which was done.
As of the time of publication, the commissioner had not responded to the questions.
A wider health crisis
The experiences documented in Anyiin are unfolding amid a prolonged conflict that has forced hundreds of thousands of people from their homes across Benue State.
The International Organisation for Migration’s Displacement Tracking Matrix (DTM) Round 18 recorded 464,543 internally displaced persons in Benue, the highest number across the North-central and North-west states covered by the assessment.
About 376,000, or 81 per cent, were living in host communities, while roughly 88,000 were in camps and camp-like settings.
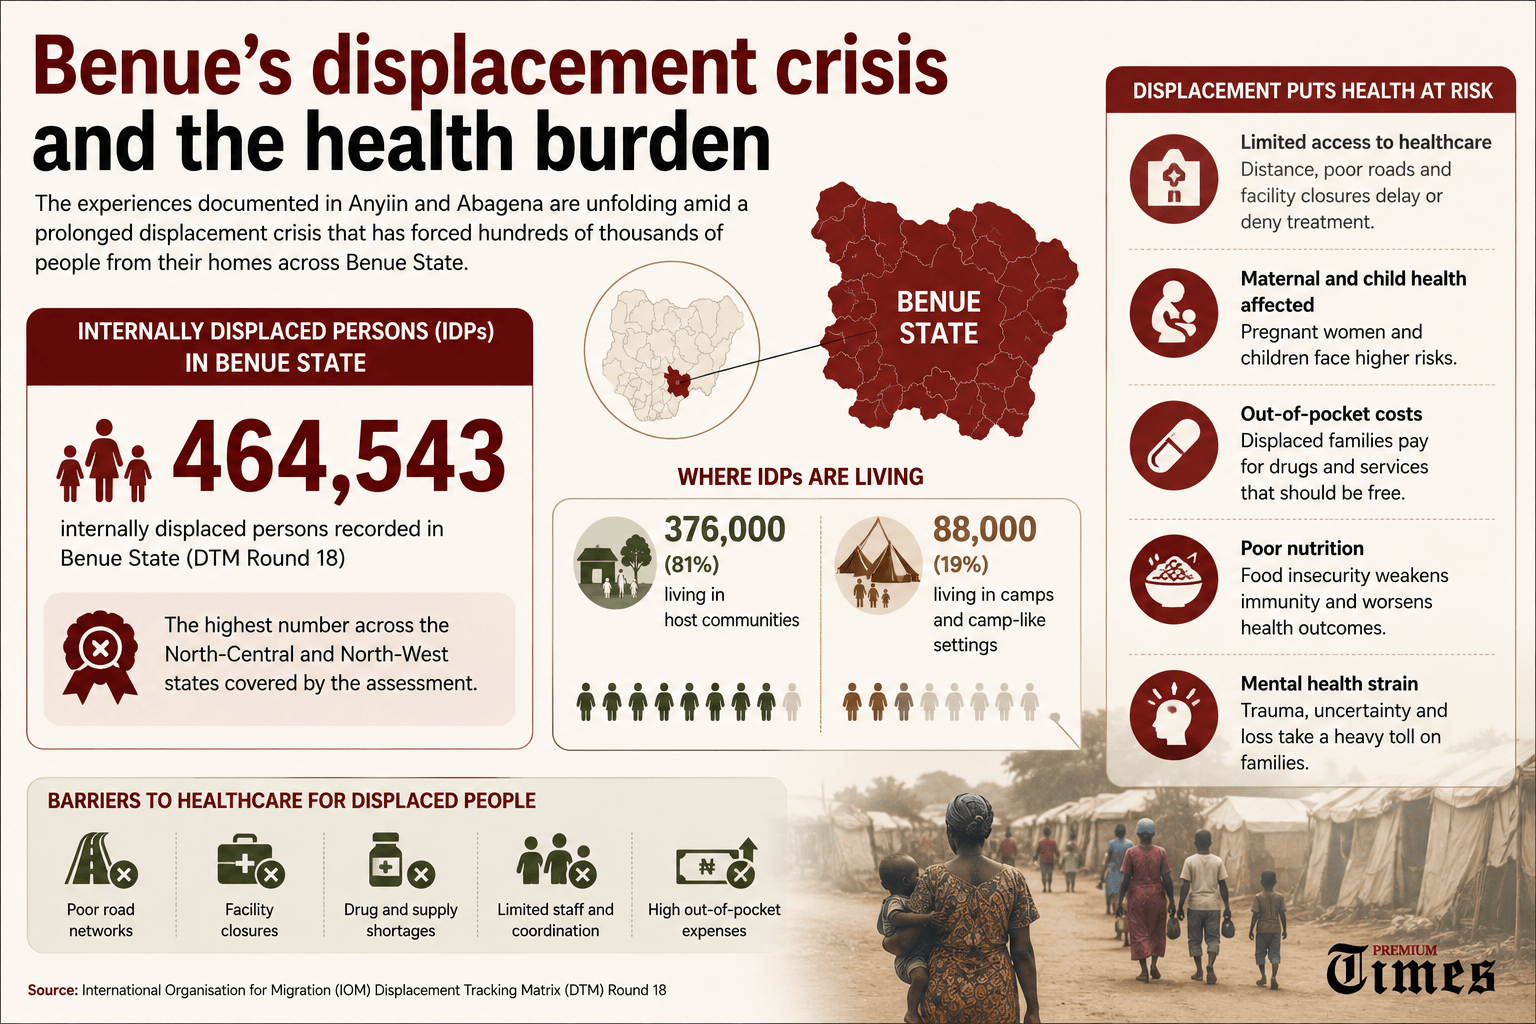
Women and children account for most of the displaced population, increasing the need for maternal, reproductive and child healthcare in the camps.
For many families, displacement has also meant the loss of farms, businesses, and other sources of income.
An August 2025 assessment by the SEMA and the Internal Displacement Solutions Fund found that 96 per cent of displaced households surveyed wanted to return to their communities.
The healthcare challenges are particularly significant for pregnant women.
A study published in the National Library of Medicine’s PubMed Central (PMC), based on research among pregnant women visiting PHCs in Benue State, reported a maternal mortality ratio of 1,189 deaths per 100,000 live births.
The study drew on data from two cohorts covering 2015–2017 and 2020–2021. The reported ratio is more than double Nigeria’s national estimate and far above the Sustainable Development Goal target of fewer than 70 maternal deaths per 100,000 live births by 2030.
ALSO READ: Inside Benue IDP camp, where thousands live with stench
Infographic: Benue’s maternal mortality burden compared with Nigeria’s national estimate and the Sustainable Development Goal target
The 2021 Nigeria Multiple Indicator Cluster Survey (MICS) found that 59.1 per cent of births in Benue State were attended by skilled health personnel.
Traditional birth attendants assisted with 17.7 per cent of births, while relatives or friends assisted with another 17.2 per cent.
Health insurance coverage among women is also low. The same survey also found that only 2.5 per cent are covered by health insurance, leaving most families reliant on out-of-pocket payments for antenatal care, medicines, and emergency treatment.
For displaced women who have lost their livelihoods, those costs are compounded by transport expenses and limited access to functioning health facilities.
Newborns face significant risks as well. According to the 2021 MICS, one in every 56 children born in Benue dies within the first 28 days of life.
Preventable illnesses, delayed care
Mr Akighir, the medical doctor and UNICEF consultant, said many illnesses affecting displaced families can be prevented or treated if care is available early.
He identified malnutrition, malaria, and acute diarrheal diseases as the major health concerns, particularly among children.
“Malnutrition is one of the biggest problems we see,” he said. “When children are malnourished, their immunity drops, and they become vulnerable to infections.”
He said poor access to safe water and sanitation can compound those risks.
“Once they start drinking untreated water, acute diarrhoeal diseases become common,” he said. “Many children also walk barefoot, exposing them to hookworm infestation, skin infections and other preventable diseases.”
Pregnant women face additional risks when poverty and displacement delay their access to care.
“Health-seeking behaviour is generally poor,” Mr Akighir said. “Sometimes labour begins, and the woman delivers inside the camp because there is nobody to accompany her to a health facility. Others present very late, when complications have already developed.”
He said weaknesses in the referral system can create further barriers, particularly for displaced people who were not registered when they arrived at the camps.
“Some of them came into the camps after registration had been completed,” he said.
“When complications arise, and they are referred, they may face challenges accessing support because they are not captured in the system.”
Support, but gaps remain
Mr Akighir said humanitarian organisations continue to support maternal and child healthcare in some of Benue’s IDP camps, including antenatal care, nutrition services, treatment of childhood illnesses and referrals for emergency care.
He said one intervention had supported more than 250 successful deliveries.
However, such interventions have not eliminated gaps in access to healthcare across the camps.
UNICEF’s 2025 humanitarian reporting shows that its health response extended beyond nutrition support. By the end of the year, the agency said essential health services had reached displaced people in 10 IDP camps and two host communities in Benue, with more than 44,000 medical consultations and 16,000 childhood immunisations recorded.
The agency nevertheless identified gaps that continued to constrain the response, including limited government funding, shortages of essential supplies and weak coordination among government agencies.
For Mrs Teryen, whose baby is due in September, those gaps have immediate consequences.
This reporting was completed with the support of the Centre for Journalism Innovation and Development (CJID).
Discover more from Premium Times Nigeria
Subscribe to get the latest posts sent to your email.
Read the full article here